Everyone in Limassol seems to know someone on a weekly weight-loss pen. Some lose 15 kilos and keep them off. Others drop the weight fast and watch most of it come back within a year of stopping. The medicine can be exactly the same; what differs is how it was used.
On average, people on weekly semaglutide lose about 15% of their body weight over a year and a half, and the newer injections go further. Which of the three medicines you take, how the dose is built up, how much of the lost weight is muscle and what happens when you stop all shape the result you keep. This guide covers semaglutide, tirzepatide and retatrutide with the numbers behind each, and explains how we run medical weight loss at Alpha Medical in Limassol.
How GLP-1 weight loss injections work
GLP-1 is a hormone your gut releases after a meal. It tells the brain you have eaten, slows the rate at which the stomach empties and helps the pancreas release insulin in proportion to the food you take in. Semaglutide (sold as Wegovy and Ozempic) copies this hormone and lasts a full week, so a single weekly injection keeps the signal switched on.
Patients describe the effect in practical terms: they feel full sooner, they stop thinking about food between meals, and portions shrink without a fight. Tirzepatide (Mounjaro, Zepbound) adds a second hormone, GIP, to the same molecule. Retatrutide goes one step further and adds glucagon, which raises the energy the body burns at rest. Each added hormone has meant more weight loss on average.
Semaglutide, tirzepatide and retatrutide: what the trials show
All three have been tested in randomised trials in adults with obesity or overweight and at least one weight-related condition. The headline numbers:
- Semaglutide 2.4 mg weekly (STEP 1, 68 weeks): average loss of 14.9% of body weight, against 2.4% on placebo
- Tirzepatide 5 mg, 10 mg and 15 mg weekly (SURMOUNT-1, 72 weeks): average losses of 15.0%, 19.5% and 20.9%, against 3.1% on placebo
- Retatrutide 8 mg and 12 mg weekly (48-week trial of 338 adults): average losses of 22.8% and 24.2%, against 2.1% on placebo, and still falling when the trial ended
- Semaglutide in people with overweight or obesity and heart disease but no diabetes (SELECT): 20% fewer heart attacks, strokes and cardiovascular deaths over about three years
Retatrutide: the triple agonist
Retatrutide acts on three receptors at once: GLP-1 and GIP, like tirzepatide, plus glucagon. The glucagon arm is the difference. It increases energy expenditure and pushes the liver to burn fat, which is why its 48-week trial also showed large drops in liver fat alongside the weight loss.
In that trial, the 12 mg dose produced a 24.2% average loss at 48 weeks, a figure that tirzepatide reached only at its highest dose after 72 weeks. The side effect pattern was similar to the other two medicines: mostly nausea, diarrhoea and vomiting during dose increases, fewer when treatment began at 2 mg rather than 4 mg. Heart rate rose slightly at higher doses, peaking around week 24 and then easing, so we check it at reviews.
Retatrutide suits patients with a large amount of weight to lose, patients with fatty liver, and those whose weight loss has stalled on semaglutide or tirzepatide.
Who these injections suit, and which one we choose
The trials enrolled adults with a BMI of 30 or more, or 27 or more with a weight-related condition such as high blood pressure, prediabetes or sleep apnoea. That is roughly who benefits most in practice.
They are a poor fit if you are pregnant, planning a pregnancy or breastfeeding, if you have had pancreatitis, or if you or a close relative have had medullary thyroid cancer or MEN2 syndrome. Patients who want to lose three or four kilos before a wedding are better served by other routes; the medicine's strength is sustained, substantial weight loss, and it takes months to show its full effect.
For most patients the choice comes down to how much weight needs to come off, what the bloodwork shows, and how the stomach tolerates the medicine. Semaglutide has the longest track record and the cardiovascular outcome data, which matters for patients with heart disease or a strong family history of it. Tirzepatide is our usual choice when a larger reduction is needed or insulin resistance is prominent on the labs. Retatrutide comes in when the goal is the largest reduction, when liver fat is high, or when progress has plateaued on one of the other two.
Our comparison of semaglutide and retatrutide goes into more detail on how those two differ.
Side effects and how we manage them
Nausea, fullness, constipation or loose stools are the common side effects. In the trials they were mostly mild to moderate and settled as the dose stabilised. The way to limit them is a slow climb: semaglutide starts at 0.25 mg a week and rises every four weeks, tirzepatide starts at 2.5 mg and rises by 2.5 mg every four weeks, and retatrutide starts at 2 mg and steps up gradually. We hold a dose for longer if the stomach needs it, since there is no prize for reaching the top dose quickly.
Eating smaller meals, stopping at the first sign of fullness, going easy on fat and alcohol, and drinking enough water deal with most of the rest. Anyone who develops severe, persistent abdominal pain on these medicines needs to be seen the same day.
Protecting muscle while the weight comes off
The scale alone is a poor measure of progress. In a body composition sub-study of the semaglutide trial, lean mass made up close to 40% of the weight lost. Some lean loss is unavoidable with any large weight reduction, but muscle is what keeps your metabolism up, your joints supported and your strength intact as you age.
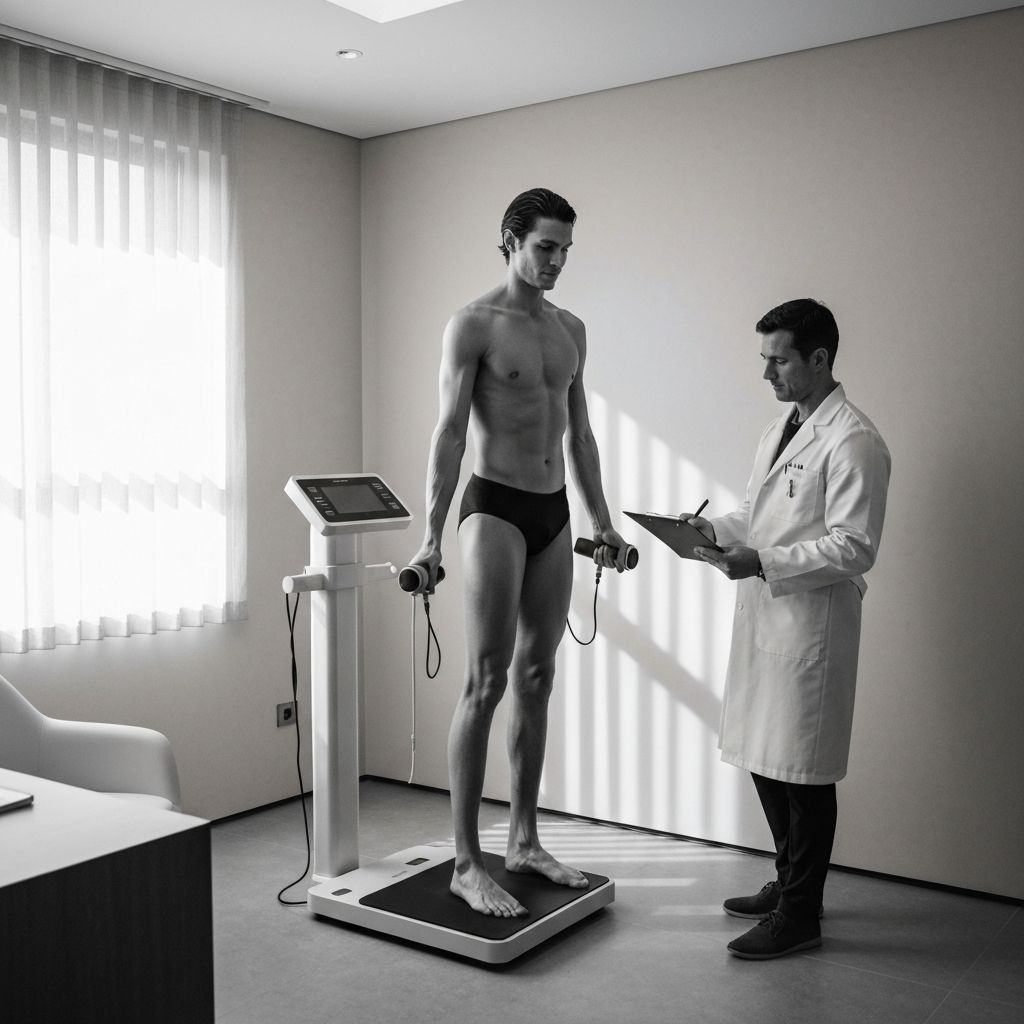
This is why we measure body composition before starting and track it during treatment. Patients get a protein target (usually 1.2 to 1.6 g per kg of target body weight a day) and a resistance training plan, and we look at the DEXA or InBody result rather than the scale alone. For men whose testosterone is low, correcting it can make a real difference to how much muscle they keep.
Keeping the weight off after you stop
One year after stopping semaglutide, participants in the STEP 1 extension had regained about two thirds of the weight they lost, and their blood pressure and blood sugar improvements faded with it. The medicine controls appetite while you take it; it does not reset it permanently.
We plan the exit from the first consultation. Most patients move to a lower maintenance dose, or space injections out gradually, rather than stopping abruptly. The habits built during treatment (protein, strength training, sleep, fewer ultra-processed foods) are what carry the result once the dose comes down, and we keep checking weight and body composition during that phase.
Medical weight loss at Alpha Medical Limassol
Every programme starts with a physician consultation about your weight history, previous attempts, medications and goals. Bloodwork follows: HbA1c, fasting glucose and insulin, lipids, liver and kidney function, thyroid, and for men a hormone panel. We add a body composition scan so we know how much of your weight is fat and how much is muscle before the first injection.
From there your physician chooses the medicine and the dose schedule, and follows you with regular reviews and repeat bloodwork. Patients come to our Limassol clinic from across Cyprus, and after the first visit many reviews can be done remotely. Weight loss is often the first step in a wider plan, followed by body contouring or skin tightening for areas the weight loss leaves behind.
Ready to take the next step? Book a consultation at our contact page — or request an introductory Medical Weight Loss guide below.